The Solution to Medicare and Social Security

My favorite radio station is public radio WLRN.  One show I enjoy most is On Point, hosted by the brilliant Meghan Chakrabarti.

Sadly, while she and her guests often lament the state of inequality and health care in America and the looming insolvency of Medicare, Medicaid, and  Social Security, they never seem to offer a solution other than cutting benefits and/or making Americans pay more.

We can do better;

———————–

The Real Limits on Federal Spending:
Healthcare, Poverty, and Inflation

Real resources are limited. Dollars are unlimited.

Two propositions should start any discussion of federal spending, healthcare, poverty, and inflation.

  1. No American should be unable to obtain needed healthcare because they lack money.
  2. No American should be forced to live in poverty merely because private income is inadequate.

These are not questions of whether the United States can “find” enough dollars. The federal government, as the issuer of the U.S. dollar, never can run short of dollars.

Alan Greenspan, Former Federal Reserve Chairman: “A government cannot become insolvent with respect to obligations in its own currency. Nothing prevents the federal government from creating as much money as it wants and paying it to somebody. The United States can pay any debt it has because we can always print the money to do that.”

The genuine economic question is whether the nation has enough real goods and services to satisfy the demand those dollars create.

That distinction changes almost everything. Federal finance commonly is discussed as though the federal government were a household, business, city, or state. Such users of the dollar must obtain dollars before they can spend them. The federal government creates the dollars it spends. Its meaningful limit therefore is not a shortage of dollars. The limit is inflation, and inflation ultimately is a problem of insufficient supply.

Inflation Is a Supply Problem

Prices rise when supply is insufficient relative to demand. When the shortage involves a product of limited importance, the result may be merely a higher price for that product. A shortage of a particular luxury handbag does not cause general inflation. But shortages of widely used necessities and inputs can spread price increases throughout the economy.

Energy is the obvious example. Oil and natural gas affect transportation, agriculture, manufacturing, chemicals, plastics, heating, electricity, and distribution. When energy becomes scarce, its higher cost is passed through to the prices of thousands of other goods and services.

Food shortages can have similarly broad effects. So can serious shortages of housing, labor, steel, shipping capacity, computer chips, or other resources that are used throughout the economy.

Wars, droughts, pandemics, crop failures, embargoes, OPEC restrictions, natural disasters, monopoly restrictions, labor shortages, housing shortages, and supply-chain failures all can create inflationary pressures without any need for “excessive” federal spending. The common element is not too many federal dollars. It is inadequate availability of important goods and services.

This is why the familiar phrase “government spending causes inflation” is misleading. It treats all federal spending as economically identical simply because it is all denominated in dollars. But the effect of spending depends on what it buys.

The Crucial Question: What Does the Spending Buy?

Suppose there is a serious oil shortage. Gasoline prices rise, transportation costs rise, and those costs work their way into food, manufactured goods, construction, and countless other prices. The federal government could respond by eliminating gasoline taxes or sending consumers checks.

Those actions would help people pay the higher prices, but they would not produce another barrel of oil. Indeed, by supporting demand for the same inadequate supply, they could let prices rise even further.

Now suppose the federal government spends the same number of dollars to attack the shortage itself: encouraging additional production where practical, expanding refining capacity, improving pipelines and distribution, developing substitute sources of energy, increasing efficiency, or removing some other bottleneck responsible for the shortage.

The number of federal dollars spent might be identical, yet the economic effect would be entirely different. The first form of spending finances competition for a shortage. The second increases the supply and therefore attacks the source of the inflation.

The important distinction, then, is not simply more federal spending versus less federal spending. It is spending that leaves shortages untouched versus spending that prevents or cures shortages. Federal spending can be inflationary, neutral, or anti-inflationary depending on its effect on the supply of the goods and services people need.

Healthcare: Financing Is Not Producing

Healthcare illustrates the distinction especially well. Millions of Americans cannot comfortably afford medical care, and public discussion treats this as though the nation lacks the dollars needed to pay doctors and hospitals. It does not.

The federal government can create all the dollars necessary to pay for healthcare. The real limitation is whether the country has enough doctors, nurses, technicians, hospitals, clinics, ambulances, laboratories, medicines, equipment, nursing facilities, home-health workers, and other medical resources.

Medicare for All therefore should have two inseparable parts. The first is financial: make necessary healthcare available regardless of the patient’s ability to pay. No one should avoid a physician, skip a prescription, postpone surgery, or face financial ruin because of illness.

The second part is productive: expand the healthcare supply enough to meet the demand created when financial barriers are removed. The federal government should finance medical education, nursing education, residency programs, training for technicians and other healthcare workers, and incentives to enter specialties and geographic areas suffering shortages. It should support construction and modernization of hospitals, clinics, laboratories, nursing facilities, and other medical infrastructure. It should finance medical research and the development and production of medicines, equipment, diagnostic systems, and treatments.

Simply giving people more ability to pay for a fixed quantity of healthcare could increase medical prices. But that is not an argument against Medicare for All. It is an argument against designing Medicare for All as nothing more than an insurance program. The answer to a healthcare shortage is to finance both access to healthcare and the production of healthcare.

The question “How can we afford Medicare for All?” therefore confuses dollars with resources. The federal government can afford the dollars. The nation must produce the healthcare.

Social Security and Poverty

The same principle applies to poverty, although the spending is less narrowly directed. No one in a wealthy nation should be forced to live in poverty because retirement, disability, unemployment, or low wages leave him or her without adequate income. A Social Security benefit sufficient to establish an income floor could eliminate much financial poverty immediately. Again, the federal government’s ability to create dollars is not the obstacle.

The inflation question is what recipients will buy and whether the economy can supply it. Additional income may increase demand for food, housing, medical care, transportation, home assistance, nursing care, recreation, and many other goods and services. Where supply can expand readily, additional demand can lead to additional production. Where supply is constrained, prices may rise.

That does not mean the government should preserve poverty in order to suppress demand. It means the government should identify the shortages and attack them. If affordable housing is scarce, increase the housing supply. If nursing-home beds are scarce, encourage construction and staffing of nursing facilities. If home-health workers are scarce, finance training and compensation sufficient to attract more workers. If transportation for the elderly is inadequate, expand it. If medical personnel are scarce, train more.

Reducing poverty by increasing income while simultaneously expanding the supply of the goods and services whose demand will rise is a far more humane anti-inflation policy than keeping people poor so they cannot bid for scarce resources.

The Wrong Cure for Inflation

Traditional anti-inflation policy often attempts to reduce demand. Higher interest rates, spending cuts, and tax increases can make borrowing and purchasing more difficult. If enough people are prevented from buying homes, cars, medical care, or other goods and services, price pressures may decline.

But this does not cure the underlying shortage. It can achieve balance by reducing the public’s ability to buy rather than by increasing the nation’s ability to produce.

If there are too few houses, one solution is to make mortgages so expensive that fewer families can buy houses. Another is to increase the housing supply. If energy is scarce, one solution is to suppress economic activity until energy demand falls. Another is to increase energy availability and efficiency. If medical services are scarce, one solution is to make medical care unaffordable for some people. Another is to produce more medical care.

The second approach grows the economy. The first just restrains it.

The Federal Budget Should Ask a Different Question

Federal programs commonly are judged by asking, “How much will this add to the deficit?” For a Monetarily Sovereign government, that question focuses attention on the wrong scarcity. Dollars are not the scarce resource. Every major federal spending proposal instead should be accompanied by a real-resource and inflation analysis.

The questions should be: What additional goods and services will this program cause people or government to demand? Are those goods and services available in sufficient quantity? Where are the likely shortages and bottlenecks? How rapidly can supply expand? What additional federal spending, incentives, research, training, construction, regulatory changes, or other measures would expand that supply?

Under such an approach,

  • Medicare for All would be paired with expansion of medical capacity. Social Security for All would be paired with attention to housing, elder care, healthcare, transportation, and other likely constraints.
  • Housing assistance would be paired with housing construction.
  • Infrastructure spending would include measures to ensure adequate supplies of skilled workers, machinery, steel, concrete, and other necessary resources.

The federal budget then would cease being primarily an exercise in pretending the government might run out of its own dollars. It would become an exercise in managing the nation’s real resources.

The Gap

This has another important consequence. The income/wealth/power Gap between the rich and the rest is not narrowed merely by telling people that desirable programs are “unaffordable.” For the federal government, affordability in dollars is not the issue. The real issue is whether increased purchasing power can be matched by increased production.

A government that understands its Monetary Sovereignty can use federal spending to provide healthcare, prevent poverty, improve education, build infrastructure, support scientific research, and expand productive capacity. Properly directed, such spending can narrow the Gap while reducing, rather than increasing, the shortages that cause inflation.

Two Principles

Much of America’s unnecessary economic suffering rests on confusion about two basic facts.

  1. First, the federal government never can run short of U.S. dollars. Taxes may serve important economic and social purposes, but the federal government does not need to collect dollars before it can create and spend dollars.
  2. Second, the true constraint on federal spending is not the number of dollars created. It is the availability of real resources. Inflation occurs when important supplies are inadequate for the demand placed upon them. Therefore, the intelligent response to inflation is to identify the shortages and cure them.

Those two principles lead to a very different conception of federal economic policy. We do not need to choose between adequate Social Security and stable prices, or between universal healthcare and stable prices. We need to finance what people require while simultaneously financing the productive capacity necessary to provide it.

The United States does not need to ration dollars. It needs to prevent shortages.

Rodger Malcolm Mitchell

When a belief is ingrained, no evidence is wanted

It is widely believed, especially among conservatives, that:
  1. Federal finances are like state/local government finances, business finances, and personal finances.
  2. It makes no difference whether a government is Monetarily Sovereign or monetarily non-sovereign.
  3. The “federal debt” is a debt of the federal government.
  4. The federal debt is owed by, and will be paid by, taxpayers.
  5. The federal debt and deficits are too large and are “unsustainable.”
  6. Federal spending should be reduced.
  7. The federal government should run a balanced budget or surplus. The federal government has borrowed and owes trillions of dollars via T-bills, T-notes, and T-bonds.
  8. The purpose of federal taxes is to fund federal spending.
    SIDE VIEW of a PLATTER WITH A MAP OF EARTH
    Once, people strongly believed the earth was flat. A few still do, despite the evidence.
  9. Medicare and Social Security will run short of funds unless taxes are increased and/or benefits are reduced.
  10. Many federal programs, for instance, poverty aid, foreign aid, global warming prevention, immigration, education, etc., are unaffordable and unsustainable.
  11. The rich don’t get richer by making you poorer.
  12. Undocumented immigrants bring crime and drugs into our country.
  13. Federal spending causes inflation.
How many of these beliefs do you have? Every one of them is wrong, proven wrong by readily available data (here, here, here, here, and elsewhere in this blog). Yet most people strongly defend one or more of these wrong beliefs, even without any evidence to support them. Here is an example of the widespread belief that immigrants harm our economy, and our way of life.

Immigration fuels US economic growth while politicians rage. Augusta Saraiva and Enda Curran, Bloomberg News While the rising number of immigrants in the U.S. has sowed division among politicians across the country — and stoked angst among a swath of voters — there’s one place where almost everyone seems on the same, upbeat page: Wall Street.

Last month, the nonpartisan Congressional Budget Office (CBO) calculated that immigration will generate a $7 trillion boost to gross domestic product over the next decade. The agency came to that conclusion after incorporating the recent surge in immigration.

The CBO release spurred a flurry of fresh number-crunching among investment bank economists to account for the boost those newcomers are giving to the labor force and consumer spending. Goldman Sachs Group Inc. revised up its near-term economic growth forecasts Sunday.

JPMorgan Chase & Co. and BNP Paribas SA were among banks that acknowledged the economic impact from surging immigration in recent weeks.

We’ll pause to remind you that Gross Domestic Product (the most common measure of our economy) = Federal Spending + Non-federal Spending + Net Exports.
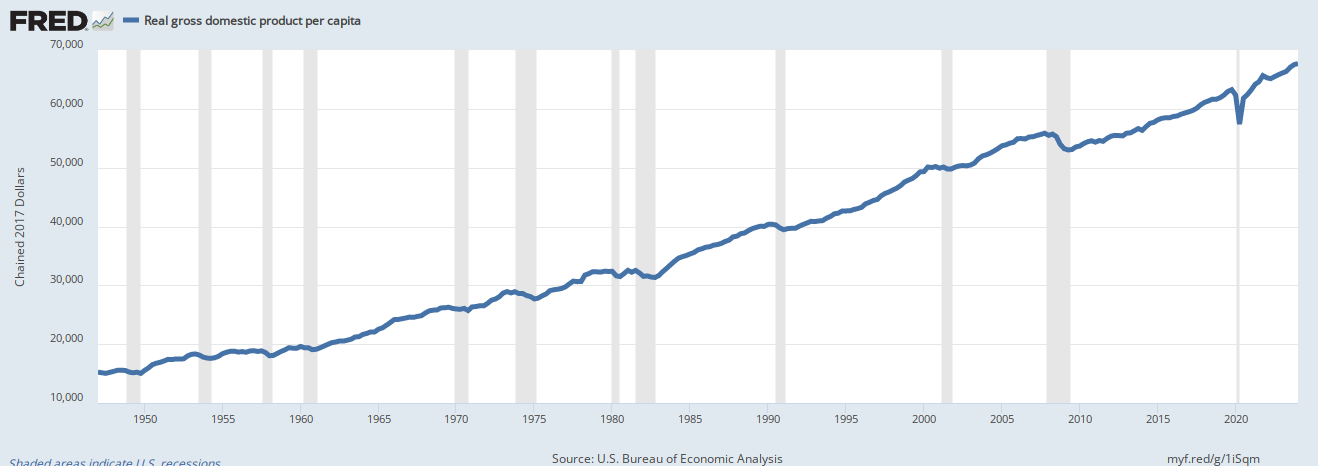
Inflation-Adjusted, Per Capita, Gross Domestic Product
Spending by immigrants increases per capita (including yours and mine) inflation-adjusted GDP. In short, immigrants make us all wealthier by working, paying local taxes, and creating and buying stuff. That is what immigrants have done for decades, and it is what has made America prosperous.

“Immigration is not just a highly charged social and political issue, it is also a big macroeconomic one,” Janet Henry, global chief economist at HSBC Holdings Plc, wrote in a note to clients Tuesday.

No advanced economy benefits from immigration quite like the U.S., and “the impact of migration has been an important part of the U.S. growth story over the past two years.”

“Two years”? More like two hundred years.

Morgan Stanley economists Sam Coffin and Ellen Zentner noted this month that faster population growth fueled by immigration leads to stronger employment and population estimates than initially thought, though they added that the full effect might not be captured by official data.

It’s hard to pin down the exact scale of the inflows of foreign-born people, thanks to many entering without visas or other documentation. But CBO statisticians incorporated data from U.S. Customs and Border Patrol to come up with their higher projected net immigration, according to Morgan Stanley analysis.

Goldman estimates that immigration was around 2.5 million in 2023, a figure that is far above the 1.6 million implied by the change in the foreign-born population in the official household survey from the Census Bureau.

The positive tone among economists contradicts that seen on the campaign trail, as a surge in the number of undocumented immigrants entering the U.S. through the southern border stokes political strife.

The share of Americans who see immigration as the most important problem facing the U.S. is now matching a record high in data going back four decades, according to a recent Gallup poll.

The recent boost from immigration is the result of both more legal immigrants as the U.S. goes through unprecedented visa backlogs and the surge in illegal border crossings.

The nation’s 32.5 million immigrant workers now account for roughly one in five U.S. workers, a record-high in government data going back almost two decades.

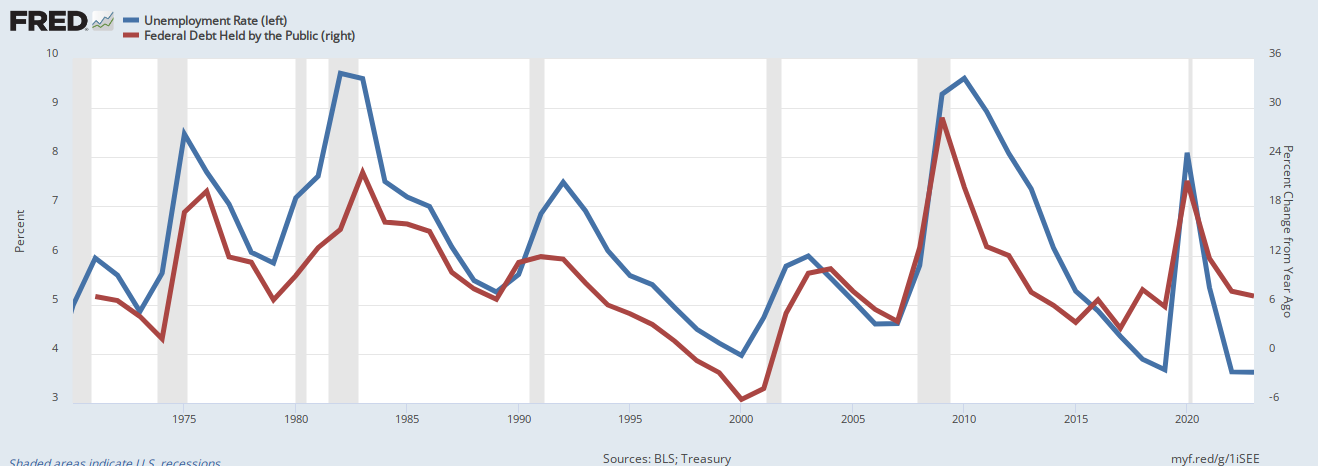
They not only are working, but their buying creates jobs. They aren’t stealing jobs as America’s xenophobes often claim. The proof: Unemployment is low “despite” (because of?) massive immigration:
Red line is federal deficits. Blue line is Unemployment. Vertical gray bars are recessions.
This interesting graph reveals several facts:
  1. When federal deficit spending declines, we have recessions.
  2. The recessions are cured by increases in federal deficit spending.
  3. The recessions cause unemployment.
  4. The unemployment, which is caused by decreases in federal deficit spending is cured by increased federal deficit spending.
Thus, unemployment is not caused by immigrants taking jobs. Quite the opposite. Unemployment and recessions have the same cause: Insufficient federal deficit spending, exactly what the conservatives want us to do.

To be sure, the connection between the higher influx of foreign workers and the rapid post-pandemic recovery has been noted by economists and policymakers alike for some time now.

The Trump GOP’s main election focus is to deport undocumented immigrants, the people who help grow America’s economy.

Federal Reserve Chair Jerome Powell has repeatedly cited immigration as one of the reasons behind strong economic growth.

In a reference to the role being played by higher labor supply, Powell pointed on Wednesday to “a strong pace” of immigration as helping on that front.

“The overall picture is a strong labor market — the extreme imbalances we saw in the early parts of the pandemic recovery have mostly been resolved, you’re seeing high job growth, you’re seeing big increases in supply,” Powell said in his press conference Wednesday.

Fed policymakers lifted their growth forecast for this year to 2.1% from 1.4%, their median estimate showed.

Businesses are ramping up calls for changes to bring in more workers through legal channels.

Almost 9 million positions are open across the economy, equal to 1.4 jobs for every job-seeker. Foreign-born workers made up a record 18.6% of the civilian workforce in 2023 and the U.S. approved a record number of work authorizations in the fiscal year through last September.

Immigration is “very policy sensitive,” Feroli cautioned, advising against extrapolating out bigger numbers beyond the end of this year. After all, policy could change after the November election, he noted.

Why does Trump and his GOP harp on immigration as America’s biggest “problem”? His success is as a fear-mongering hate-mongerer. When he preaches hatred toward Muslims, Mexicans, gays, blacks, people from “shithole” countries — when he lies that they bring crime, drugs to America, he is preaching to people he has frightened with his bigotry. He creates scapegoats, and then claims he will deal with them. Hitler did it. All dictators do it. The facts are:
  1. Immigrants are less likely to commit crimes than are citizens.
  2. Illegal drugs enter the U.S. through legal channels, not via undocumented immigration.
False beliefs, especially those repeated for months and years, are difficult to dislodge with facts. But ultimately, that is all you can do. Just as a lie gains strength the more it is repeated, so does the truth. Learn the truths and repeat them again and again. It’s the only way to defeat the Hitlers of the world. Rodger Malcolm Mitchell Monetary Sovereignty Twitter: @rodgermitchell Search #monetarysovereignty Facebook: Rodger Malcolm Mitchell

……………………………………………………………………..

The Sole Purpose of Government Is to Improve and Protect the Lives of the People.

MONETARY SOVEREIGNTY

You could have comprehensive, no deductible Medicare for all. Why does the AARP tell you otherwise?

I believe the people at AARP understand that our government, being Monetarily Sovereign, never can run short of its own sovereign currency, the U.S. dollar.

They must know that even if all federal tax collections — income taxes, payroll taxes, etc. — and every other form of federal government income totaled zero, the government could continue spending forever.

The sole purposes of federal taxes (unlike state, local taxes) are not to provide the government with spending money, but:

  1. To control the economy by taxing what the government wishes to discourage and by giving tax breaks to what the government wishes to reward.
  2. To assure demand for the U.S. dollar by requiring taxes to be paid in dollars
  3. And the hidden reason: To help the very rich become richer by widening the Gap between the rich and the rest.

Stated simply, the U.S. federal government can pay for anything it wishes without taxing anyone.

AARP claims it “is the nation’s largest nonprofit, nonpartisan organization dedicated to empowering Americans 50 and older to choose how they live as they age. Advocating for people age 50-plus is at the heart of our mission.”

So why does the AARP repeatedly indicate the federal government can’t afford to pay for a comprehensive, no deductible Medicare benefit for every man, woman, and child in America?

Could their lucrative insurance business be the reason? 

Here are excerpts from an article in the October, 2023 AARP Bulletin: (By Dena Bunis, who covers Medicare, health care, health policy and Congress. She also writes the Medicare Made Easy column for the AARP Bulletin. An award-winning journalist, Bunis spent decades working for metropolitan daily newspapers, including as Washington bureau chief for The Orange County Register and as a health policy and workplace writer for Newsday.)

For decades, as Americans approached their 65th birthday, all they had to do to get Medicare, the nation’s government-sponsored health insurance for older adults, was sign up.

The program wasn’t all that complicated. You went to the doctor armed with your Medicare card. Your physician or hospital took care of you and billed Medicare. Then you — or the supplemental (Medigap) plan you bought — paid your out-of-pocket share. Easy.

Today’s Medicare isn’t your grandparents’ program. New enrollees have an immediate big decision to make: Should they enroll in original Medicare (also referred to as traditional Medicare) or sign up for the private insurance managed care alternative, Medicare Advantage (MA)?

But why? Why is a decision needed?

AARP doesn’t explain why there are two plans, and why people are forced to choose between them. AARP also doesn’t explain why everyone, young or old must pay for some form of healthcare insurance, or have an employer pay.

In short, AARP doesn’t discuss the true question: Why doesn’t the federal government simply pay for everyone’s healthcare? 

AARP profits by providing in their words, “health security, financial stability and personal fulfillment. AARP also works for individuals in the marketplace by sparking new solutions and allowing carefully chosen, high-quality products and services to carry the AARP name.” 

Clearly, Medicare for All would be a financial disaster for AARP.

The two options not only differ in how they operate but increasingly in what coverage and services they provide. Making the decision requires looking down two roads that more and more are heading in different directions.

Original Medicare’s biggest draw remains the freedom enrollees have to go to any doctor or hospital in the country that takes Medicare.

In most cases, you don’t need a referral to go to a specialist or get a covered procedure done. It’s a simple fee-for-service insurance structure that was once commonplace across America but has mostly vanished for those under 65.

In Medicare Advantage, plans can feel more familiar, as they closely resemble the managed care plans offered by many employers, often in the form of a health maintenance organization (HMO) or preferred provider organization (PPO).

An MA plan is the one-stop-shopping alternative that bundles hospital, doctor and prescription drug coverage.

Most offer extra benefits not in original Medicare. MA plans also cap how much beneficiaries must pay out of pocket each year, something original Medicare does not.

The sole purpose of government is to improve and protect the lives of the people. That said, there is no reason why a federally funded plan cannot do everything Medicare + Medicare Advantage + every company-funded plan does — and without charging the American people one cent.

That is one way our government should improve and protect our lives.

(And no, this isn’t “socialism,” which is government ownership and control. It’s merely government funding, which is what the government currently does millions of times a day.)

Another big difference: Original Medicare is managed entirely by the federal government (oversight by Congress, day-to-day operations by the Centers for Medicare & Medicaid Services (CMS), meaning it is not operated for a profit.

That’s not exactly correct.  The payment is managed by the government, but the services come from the private sector. The doctors, hospitals, the technicians, etc. are in the private sector.

The exception is the VA health system, which is owned and operated by the federal government.

Advantage plans, by contrast, are operated by private and often for-profit organizations that get flat-rate payments from the government to provide health care to an enrollee. 

The financial difference is more apparent than real. The federal government still pays, but with Medicare Advantage, private insurance companies and their profit requirements are inserted as (unnecessary) middlemen between the providers and the government.

MA’s promise of extra benefits and lower premiums has been effective. In 2008, only 22 percent of beneficiaries were in Advantage plans. Since then, enrollment in these managed care plans has more than doubled and continues to grow.

In 2023, more than half of Medicare’s 60 million beneficiaries who have both Medicare parts A and B are enrolled in an MA plan.

And that’s the irony of the entire system. The government pays for both medical plans, but they offer different benefits. Medicare could (and should) offer the same or even better benefits MA offers. But it doesn’t.

Why? Because Americans have been brainwashed into believing that Medicare “can’t afford” to provide such benefits, and that in some mysterious way, Medicare can run out of money.

Medicare now finds itself at a crossroads. Based on current patterns, it won’t be long before enrollment in MA plans substantially overtakes enrollment in original Medicare.

Does the original need to be changed to remain competitive with MA? More fundamentally, will original Medicare as envisioned by President Lyndon Johnson and Congress in 1965 cease to exist in the years to come?

“I genuinely do believe that the future of Medicare lies in Medicare Advantage,” says James E. Mathews, executive director of the Medicare Payment Advisory Commission (MedPAC), established by Congress to analyze the program and provide advice. Mathews expects there will be a “natural migration” to MA, but he’s not sure whether that means original Medicare will disappear.

“It remains to be seen whether there is going to be some subset of the Medicare population for whom Medicare Advantage simply will not work.”

Medicare and Medicare Advantage will work if the benefits of both plans are blended into a Medicare for All plan.

Preserving and strengthening Medicare is one of AARP’s key policy concerns. That includes maintaining original Medicare.

“We strongly believe that traditional Medicare should be protected and strengthened and that there has to be a level playing field between traditional Medicare and Medicare Advantage,” says Megan O’Reilly, AARP vice president for health and family issues.

CMS Administrator Chiquita Brooks-LaSure oversees all Medicare operations. She says her priority is to strengthen both options. “I believe it’s critical that people have a choice between traditional original Medicare and Medicare Advantage,” Brooks-LaSure said in an interview with AARP.

It’s like claiming that people should have a choice between an all-meat diet and an all-vegetable diet. Most people would prefer to blend the two into one complete plan.

Even experts who are most bullish on Medicare Advantage say they don’t expect original Medicare to go away. The main reason is choice.

centers for medicare and medicaid services administrator chiquita brooks la sure

Chiquita Brooks-LaSure, Administrator of the Centers for Medicare & Medicaid Services. Does she really not know that the federal government can fund one plan that offers every benefit?

The case for keeping original Medicare

Under original Medicare, you can go to any doctor, lab or hospital in the U.S. that participates in the program (about 90 percent of medical professionals do).

In MA plans, enrollees mostly must go to providers within the plan’s network, and these networks are highly regionalized. Going out of network means facing a much higher copay for each visit. In some cases, the care may not be covered at all.

“There are always going to be a lot of people who are going to say, ‘Look, I want to go to a doctor I want, and I don’t want to be limited,’ ” says Tom Scully, who was CMS administrator from 2001 to 2003 and is a supporter of Medicare Advantage. As a result, “I think original Medicare will never go away.”

“I believe it’s critical that people have a choice between traditional original Medicare and Medicare Advantage.”

— Chiquita Brooks-LaSure, CMS Administrator

Until they enroll, many Americans don’t realize how costly and complicated Medicare can be. That is especially true if you choose original Medicare.

Most original enrollees must make three regular insurance payments: one for basic Part B coverage, one for a Part D prescription plan, and one more for a Medigap policy to cover some or all of the expenses that Medicare doesn’t.

And there are other expenses on top of the premiums; for example, original Medicare Part B has an annual deductible ($226 in 2023); there’s also a deductible for every hospital visit, which in 2023 is $1,600. Those charges take a heavy financial toll.

All those premiums, deductibles an lack of coverage are unnecessary. The federal government could, and should fund one program encompassing all benefits. Why force people to forego some benefits?

By contrast, an Advantage plan enrollee usually has just one recurring payment: It includes the government-mandated Part B coverage cost and, in some cases, a small additional premium, which varies by what plan you choose and where you live.

You pay various copays and deductibles for your services and doctor visits, but the rest is fully covered by the plan, and you know going in what the copay is for the different providers. Costs under MA can also add up, though, especially if you need hospital care; most plans have a per-day hospital charge.

An important dividing line when choosing a Medicare path is whether a beneficiary can afford to pay the added monthly costs of a Medigap policy to supplement original Medicare coverage, as well as for a separate Part D prescription plan.

The federal government could and should pay for the above coverages.

The difference in “choice” between original Medicare and an MA plan isn’t simply which doctor you can see.

In an MA plan, the care you need is likely to be more scrutinized than in an original plan.

Insurers that run MA plans often require what’s called prior authorization before paying for your tests and procedures; that means a doctor must get approval for recommended care from internal reviewers before the treatment will be covered.

Why does MA require prior authorization, while Medicare does not? MA is ruled by the profit motive, while Medicare is ruled by the political motive.

MA can refuse unprofitable procedures. Medicare can afford to fund procedures that have political support, regardless of cost.

Some MA plans also require referrals to specialists, meaning if you wish to see, say, a cardiologist, you’ll need your primary care doctor’s blessing.

People in original Medicare usually don’t need referrals to see specialists, and as long as Medicare covers a test or treatment a doctor orders, except in a few situations, Medicare will pay for it.

If you develop a health condition that requires specialized surgery or highly advanced therapies to treat; in an MA plan, you likely won’t be coveredif you seek care from a doctor or medical center that specializes in your issue but is out of the network.

The above is the result of the profit motive taking precedence.

On the other hand, most MA plans have benefits that original Medicare does not. The out-of-pocket cap is a big one; in 2023, MA enrollees know they won’t have to pay more than $8,300 in total annual health costs, although many plans have lower out-of-pocket limits than that.

Once again, there is no out-of-pocket cap in original Medicare.

Why are people subject to any out-of-pocket costs, when the federal government has infinite money to pay for medical care? No reason outside of the false claims that the federal government can run short of money.

Most MA plans cover basic dental, vision and hearing services.

Why does Medicare not cover dental, vision and hearing? Again, no good reason. Just the Big Lie about federal finances. 

Some provide what are called Medicare flex cards that beneficiaries can use to pay for over-the-counter medications and other drugstore items, as well as healthy food.

In recent years, Congress began allowing MA plans to pay for making improvements to beneficiaries’ homes, such as wheelchair ramps and shower grips in bathrooms. Some plans pay for gym membershipsor transportation to doctors’ offices.

These are benefits the federal government could and should support; they increase the health of the people.

David Lipschutz, associate director of the Center for Medicare Advocacy, supports the ability of Medicare to help pay for nonmedical services that can help keep an older American healthy.

But he says it’s not fair that enrollees must be in a Medicare Advantage plan to take advantage of those extras. “One should not be forced to enroll in a private plan to access such services,” Lipschutz says.

No, it’s not fair that people should be forced to pay for any medical benefits when the federal government has the infinite ability to pay.

Imagine you have a few trillion dollars to your name, and your daughter needs expensive surgery. Would you pay for her the life-saving health care? The government has many trillions. It should follow its mandate to protect our lives.

Advocates and patients agree that MA plans seem fine as long as you’re healthy. But too often, beneficiaries with serious illnesses find it more difficult to get the care they say they need.

A 2022 report from the Government Accountability Office (GAO), a congressional watchdog, found that “Medicare Advantage beneficiaries in the last year of life left the program to join traditional Medicare at twice the rate of other beneficiaries. This could indicate potential problems with their care.”

The profit motive incentivizes private insurance companies to be excellent premium  collectors but reluctant health care providers.

“Denials may be more frequent in Medicare Advantage plans than in traditional Medicare for people who have serious health problems,” says Tricia Neuman, senior vice president and head of the Medicare program at KFF, formerly the Kaiser Family Foundation.

That could be a real concern. When people age into Medicare, they tend to be healthier than they will be as they grow older and have more health problems, and that may not be top of mind.”

A federally funded, comprehensive, no-deductible Medicare for All would not have that problem.

Original Medicare may have another disadvantage: television. Throughout the year, but most prominently during Medicare open enrollment season each fall, ads for Medicare Advantage plans blanket broadcast and cable television stations.

From NFL Hall of Famer Joe Namath to “Captain Kirk” William Shatner to Jimmie Walker of “dy-no-mite” fame, celebrities urge older adults to call an 800 number and get lots of extras and benefits from Medicare Advantage plans.

Individual insurers also run ads, and some Medigap plans take to the airwaves. There are no such commercials for original Medicare.

Plenty of money for advertising; not enough for benefits.

“There’s nothing that helps lay out the trade-offs” between original and Medicare Advantage, says Gretchen Jacobson, vice president of Medicare at the nonpartisan Commonwealth Fund. “So if you just pay attention to the Medicare Advantage marketing, you may not really understand what the advantages and disadvantages are.”

To address confusion, CMS announced a crackdown this year on misleading Medicare ads.

“When we did focus groups with brokers, many said they are paid more to put people into Medicare Advantage plans, sometimes much more”

— Gretchen Jacobson, vice president of Medicare at the nonpartisan Commonwealth Fund.

And here is where the profit motive really comes into play:

“When we did focus groups with brokers, many said they are paid more to put people into Medicare Advantage plans, sometimes much more,” Jacobson said. But “if they were going into Medicare tomorrow, most of them said they would choose to be in traditional Medicare.”

These brokers do not get any commission for helping someone enroll in original Medicare. Likewise, they said most Part D prescription plans don’t offer commissions; for those that do, the rate is low.

As for Medigap policies, an agent might get some money for signing people up, but agents say it’s not as much as what they get for a Medicare Advantage enrollment.

The combination of insurance company advertising and insurance broker commissions puts people into Medicare Advantage, when that may not be the wisest choice, and certainly not the least expensive choice (which would be federally funded Medicare for All).

SO WHY NOT?

Here are the cons, per ProCon.org:

  1. Universal health care for everyone in the United States promises only government inefficiency and health care that ignores the realities of the country and the free market.

“The VA system is not only costly with inconsistent medical care results, it’s an American example of a single-payer, government-run system.

We should run from the attempts in our state to decrease competition in the health care system and increase government dependency, leaving our health care at the mercy of a monopolistic system that does not need to be timely or responsive to patients.

The above supposedly is a negative about Medicare for All, except it isn’t. It is a negative about something no one proposes: VA-style federally owned and operated hospitals with providers being employees of the government.

It’s a fake, perhaps intentionally misleading, negative that no one wants. Medicare for All would be federally funded, not owned and operated. It would be an expanded version of Medicare without the FICA tax.

2. The challenges of universal health care implementation are vastly different in the U.S. than in other countries, making the current patchwork of health care options the best fit for the country.

Though the majority of post-industrial Westernized nations employ a universal healthcare model, few—if any—of these nations are as geographically large, populous, or ethnically/racially diverse as the U.S.

Different regions in the U.S. are defined by distinct cultural identities, citizens have unique religious and political values, and the populace spans the socio–economic spectrum. Moreover, heterogenous climates and population densities confer different health needs and challenges across the U.S.

Thus, critics of universal healthcare in the U.S. argue that implementation would not be as feasible—organizationally or financially—as other developed nations.”

Yes, blah, blah, blah, America is too big, too diverse, too climate-challenged, all great arguments except for one small detail. Medicare already has solved those fake problems. It funds health care all over our big country, and is quite popular, thank you.

3. Government control is a large driver of America’s health care problems.

Bureaucrats can’t revolutionize health care – only entrepreneurs can. By empowering health care entrepreneurs, we can create an American health care system that is more affordable, accessible, and productive for all,” explains Wayne Winegarden, Senior Fellow in Business and Economics, and Director of the Center for Medical Economics and Innovation at Pacific Research Institute.

Someone please tell Mr. Winegarden that bureaucrats wouldn’t be in charge of revolutionizing anything. They merely would write the checks, just as they do now for Medicare.

4. Universal health care would increase wait times for basic care and make Americans’ health worse.

If coverage was nearly universal, cost sharing was very limited, and the payment rates were reduced compared with current law, the demand for medical care would probably exceed the supply of care–with increased wait times for appointments or elective surgeries, greater wait times at doctors’ offices and other facilities, or the need to travel greater distances to receive medical care. Some demand for care might be unmet.

Rephrasing the objection: “If everyone could get free healthcare, there wouldn’t be enough doctors, nurses, and hospitals to treat us rich folks. It’s better that some poorer people do without, so we don’t have to.”

The same objection could have been made to original Medicare. 

However, if the federal government, which can afford anything, pays enough to those doctors, nurses, and hospitals, more people will enter the profession and more hospitals will be built.

It is a fake objection, the purpose of which is to widen the income/wealth/power Gap between the rich and the rest.

5. Universal health care would raise costs for the federal government and, in turn, taxpayers.

Medicare-for-all, a recent universal health care proposal championed by Senator Bernie Sanders (I-VT), would cost an estimated $30 to $40 trillion over ten years.

The cost would be the largest single increase to the federal budget ever.

Here, we have come to the Big Lie in economics, the lie that federal taxes fund federal spending. It is a lie promulgated by the very rich to discourage those who aren’t rich from asking for benefits.

The rich use the confusion between monetarily non-sovereign local and state governments vs, Monetarily Sovereign federal government.

State and local governments cannot create dollars at will, so they rely on tax income to fund their spending. The federal government can create dollars at will, so it does not use tax dollars. In fact, the federal government destroys all your tax dollars upon receipt.

You pay your taxes with dollars from your checking account which are part of the M2 money supply measure. Once your tax dollars reach the U.S. Treasury, they no longer are part of any money supply measure. They effectively are destroyed.

The Federal Reserve creates dollars at will by purchasing securities from a bank (or securities dealer) and paying for the securities by adding a credit to the bank’s reserve (or to the dealer’s account) for the amount purchased. In short, the Fed creates dollars from thin air, whenever it wishes.

Former Fed Chair Alan Greenspan: “A government cannot become insolvent with respect to obligations in its own currency. There is nothing to prevent the federal government from creating as much money as it wants and paying it to somebody. The United States can pay any debt it has because we can always print the money to do that.”

Former Fed Chair Ben Bernanke: “The U.S. government has a technology, called a printing press (or, today, its electronic equivalent), that allows it to produce as many U.S. dollars as it wishes at essentially no cost.”

Thus, the federal government can, at the touch of a computer key, fund a free, comprehensive, no deductible, Medicare program to protect every man, woman, and child in America.

SUMMARY

There is not a single financial reason why the government doesn’t improve and protect the lives of the people’s health, one of the jobs for which it was formed.

Every argument against free Medicare for all is based on ignorance and/or a lie. In creating Medicare, we already have done the hard part. It is only left to us to expand Medicare while ending all medical taxes and fees, and voila, we have Medicare for All.

Sadly, the rich and the insurance companies prevent the government from doing its job.

You don’t have free, comprehensive, no-deductible health care. Don’t blame “insolvency,” lack of money, inflation, lack of caregivers, or any other factor.

Blame the rich and the private insurance providers like AARP et al, for promulgating the Big Lie.

And blame yourself for believing it.


Rodger Malcolm Mitchell
Monetary Sovereignty

Twitter: @rodgermitchell Search #monetarysovereignty
Facebook: Rodger Malcolm Mitchell

……………………………………………………………………..

The Sole Purpose of Government Is to Improve and Protect the Lives of the People.

MONETARY SOVEREIGNTY

Absolute proof we need more people with guns in America

“A well-regulated Militia, being necessary to the security of a free State, the right of the people to keep and bear Arms, shall not be infringed.”

Now that the Supreme Court, in its great wisdom, has decided that the first thirteen words of the 2nd Amendment, unlike every other word in the Constitution, are useless, meaningless, and to be ignored, we can get on with the job of arming every man, woman, and child with high-powered weapons.

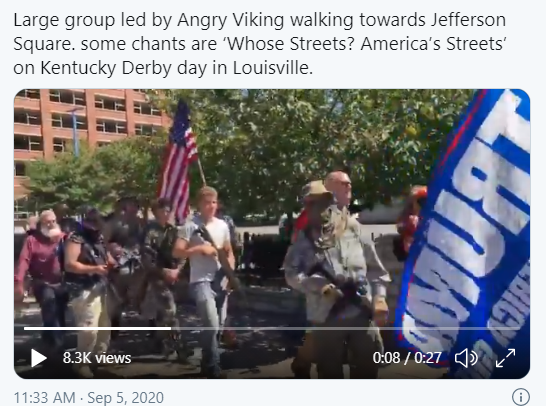
Thank goodness, we can count on these guys to protect America.

Armed right-wing activists and militia members gather in Louisville, Kentucky, US, September 5, 2020 © Reuters / Bryan Woolston

Heavily armed 400 members of the NFAC (Not Fucking Around Coalition) black militia marches in Lafayette, LA, August 21, 2020


Heavily-armed protesters wearing Proud Boys and Black Guns Matter masks entered the Michigan Capitol Thursday to defend their Second Amendment rights, as lawmakers continue to debate whether to ban guns from the building. Around 1,000 demonstrators gathered on the state Capitol lawn in Lansing throughout the day as part of the annual Second Amendment March that celebrates their right to open carry firearms across the state. Many protesters had AR-15 rifles slung over their shoulders, while many sported paraphernalia in support of extreme right-wing groups and Donald Trump.

There are scores of armed groups, with thousands of members who identify themselves as “militias,” though they are not “well-regulated,” as the useless and meaningless words in the Constitution demand.

From the look of those heavily-armed, “militia” people, perhaps the Supreme Court might have second thoughts about ignoring the well-regulated phrase.

But, I’m sure these guys will come to your defense if the crazy libs force you to receive Medicare, Social Security, and unemployment benefits.

What do you think?

Rodger Malcolm Mitchell

Monetary Sovereignty Twitter: @rodgermitchell Search #monetarysovereignty Facebook: Rodger Malcolm Mitchell …………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………..

THE SOLE PURPOSE OF GOVERNMENT IS TO IMPROVE AND PROTECT THE LIVES OF THE PEOPLE.

The most important problems in economics involve:

Ten Steps To Prosperity:

  1. Eliminate FICA
  2. Federally funded Medicare — parts A, B & D, plus long-term care — for everyone
  3. Social Security for all or a reverse income tax
  4. Free education (including post-grad) for everyone
  5. Salary for attending school
  6. Eliminate federal taxes on business
  7. Increase the standard income tax deduction, annually. 
  8. Tax the very rich (the “.1%”) more, with higher progressive tax rates on all forms of income.
  9. Federal ownership of all banks
  10. Increase federal spending on the myriad initiatives that benefit America’s 99.9% 

The Ten Steps will grow the economy and narrow the income/wealth/power Gap between the rich and the rest.

MONETARY SOVEREIGNTY